Navigating Medicare Advantage Problems: Challenges, Risks, and Solutions for 2026

Medicare Advantage (Part C) plans often entice beneficiaries with low premiums and extra benefits like dental or vision coverage. However, these private-sector alternatives to Original Medicare present significant challenges, including restricted provider networks, frequent prior authorization delays, and limited portability when attempting to return to Original Medicare with supplemental coverage. Understanding these systemic hurdles is essential for managing your healthcare effectively in 2026.
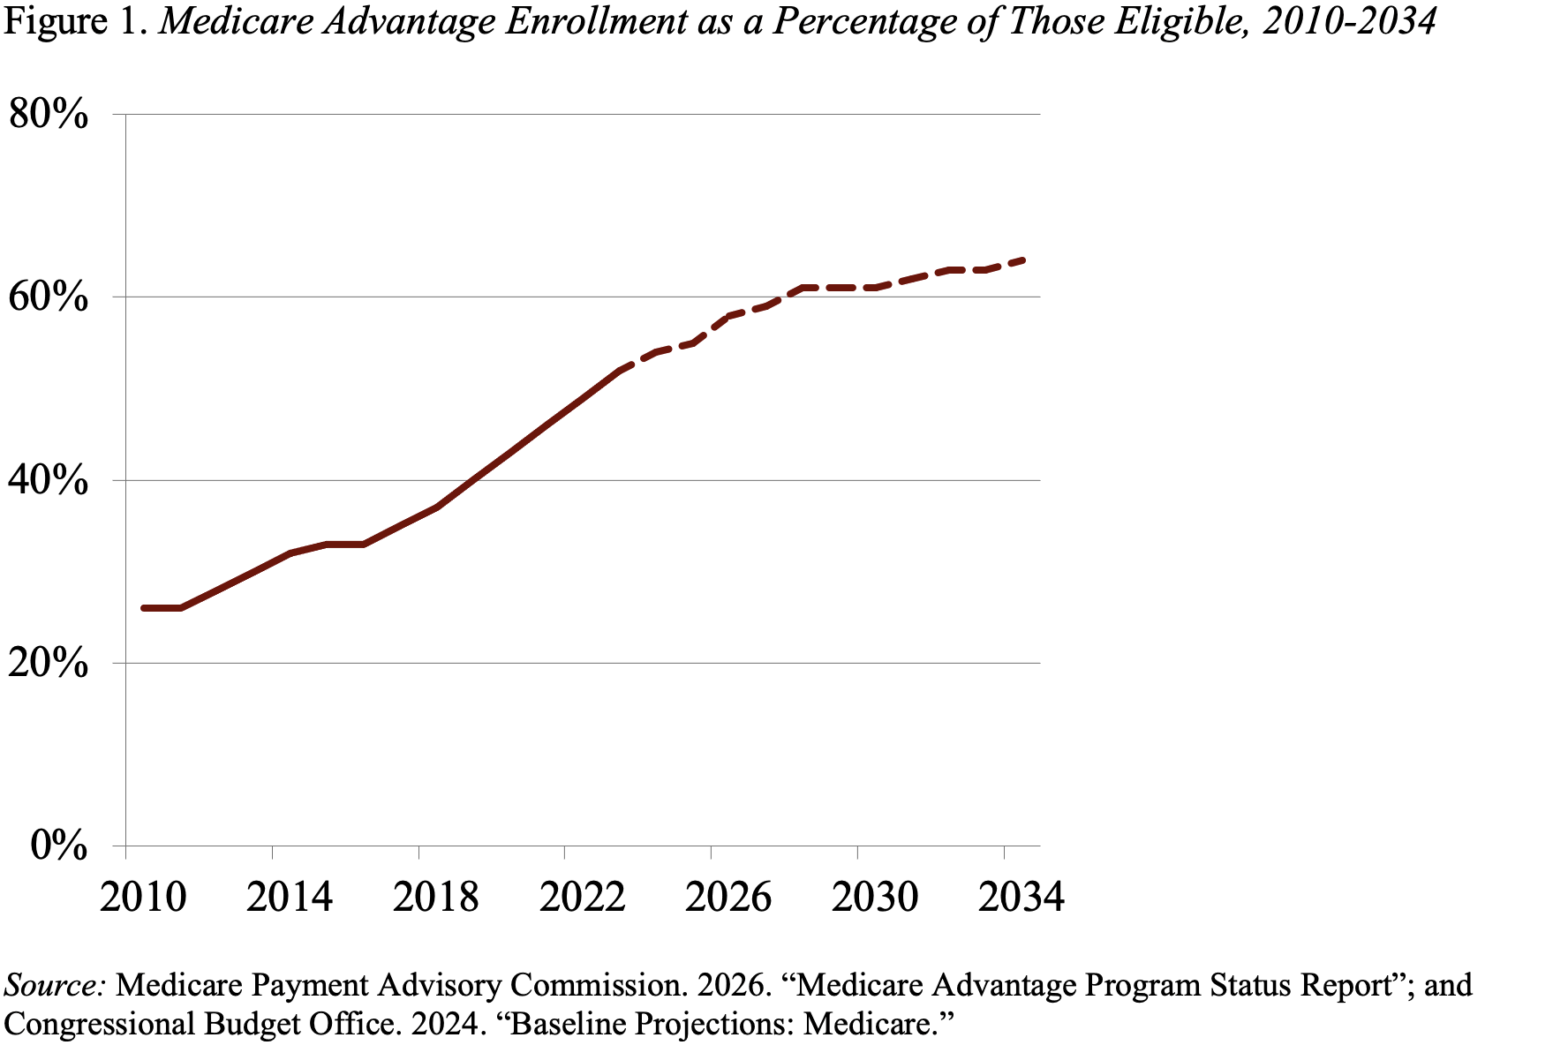
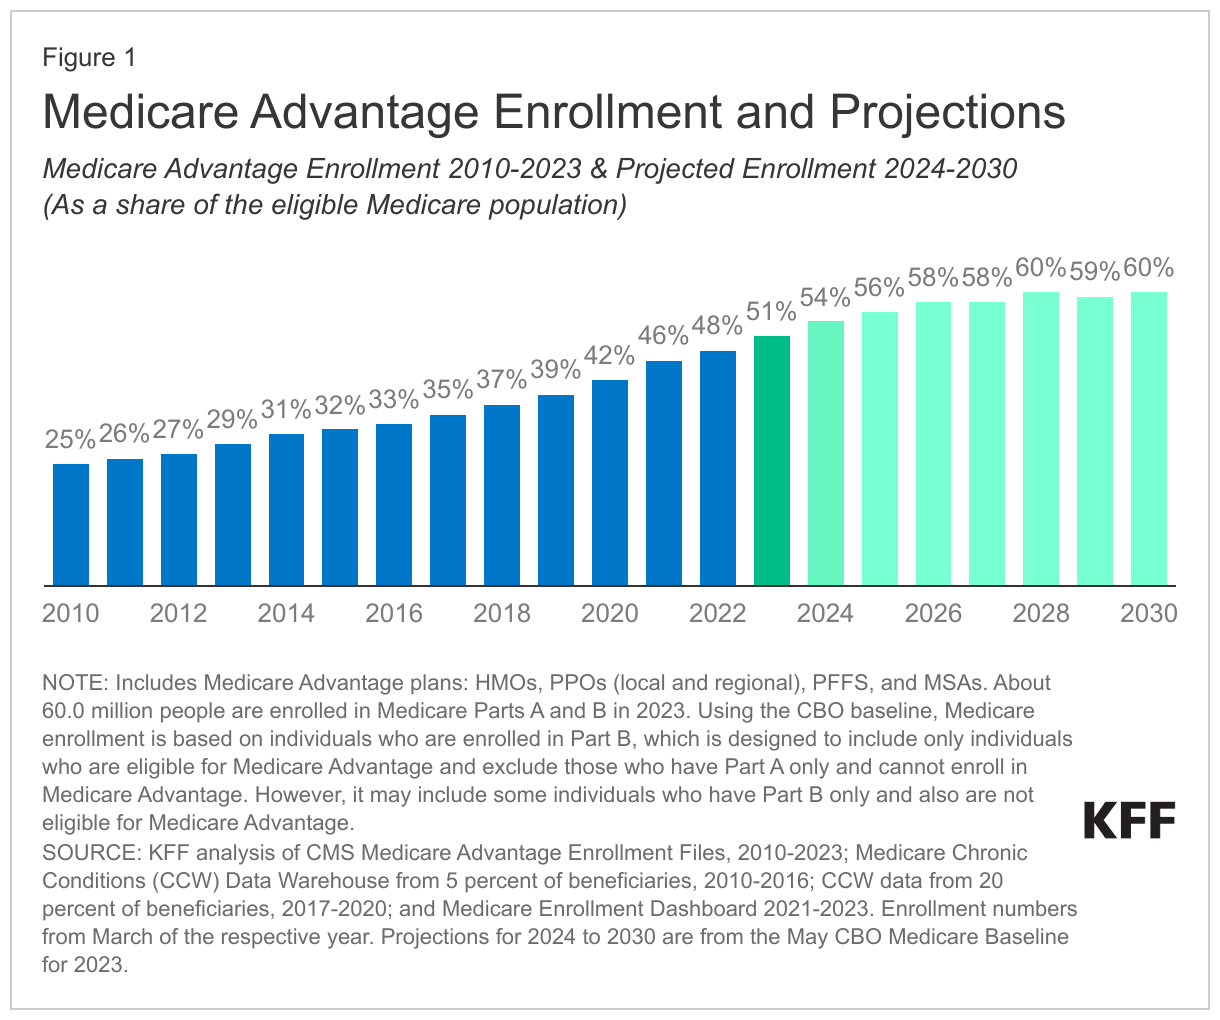
Medicare Advantage has grown to encompass more than half of the eligible Medicare population. While the bundled nature of these plans—combining Part A, Part B, and usually Part D—appeals to many for its simplicity, the "managed care" model introduces friction that does not exist in the traditional fee-for-service system. As we navigate the 2026 plan year, beneficiaries must look beyond the marketing gloss to understand the operational realities of these plans.
Restricted Provider Networks and the "Ghost Network" Crisis
One of the most persistent Medicare Advantage problems involves the limitations placed on where and from whom you can receive care. Unlike Original Medicare, which is accepted by nearly every doctor and hospital in the United States, Medicare Advantage plans utilize specific provider networks.
The HMO vs. PPO Limitation
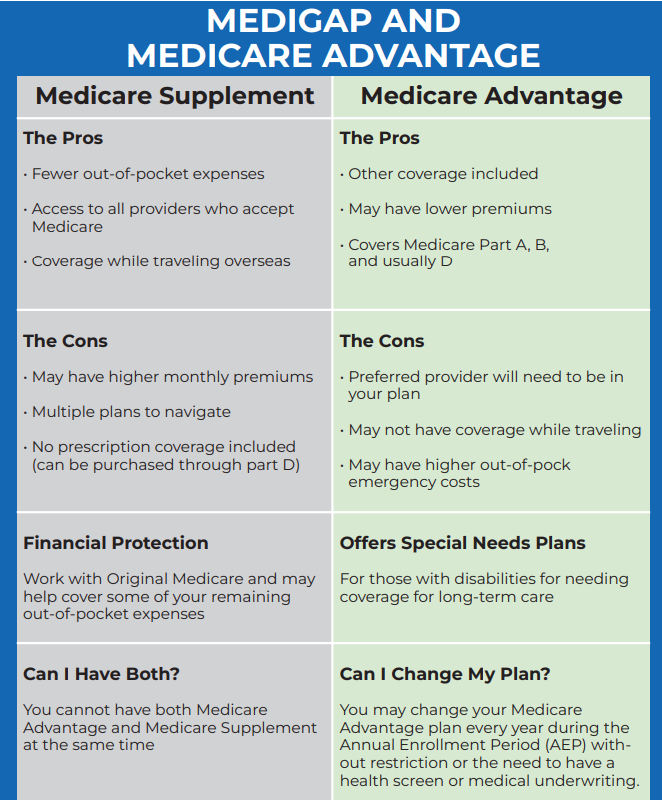
Most plans are structured as Health Maintenance Organizations (HMOs) or Preferred Provider Organizations (PPOs). In an HMO, you are generally restricted to a specific group of doctors and must obtain a referral from a primary care physician to see a specialist. If you seek care outside this network, the plan may not cover the costs at all, except in emergencies. PPOs offer more flexibility but charge significantly higher cost-sharing (copayments and coinsurance) for "out-of-network" services.
The Prevalence of Ghost Networks
A significant technical issue in 2026 remains the "ghost network" phenomenon. This occurs when a plan’s provider directory lists doctors as "in-network" who are actually no longer participating, are not accepting new patients, or have retired. Research and regulatory audits by the Centers for Medicare & Medicaid Services (CMS) have consistently shown that directory accuracy is a major pain point. For a beneficiary, this can lead to delayed care or unexpected medical bills when they discover a specialist is actually out-of-network after an appointment has been scheduled.
Prior Authorization and Care Denials
The most scrutinized Medicare Advantage problem involves the use of prior authorization. This is a process where the insurance company must approve a service, procedure, or medication before it is performed for the cost to be covered.
Utilization Management as a Barrier
While insurers argue that prior authorization prevents unnecessary medical procedures and controls costs, patients and providers often view it as a barrier to necessary care. In 2026, despite new CMS regulations intended to streamline the process, many beneficiaries still face "denial of care" for services that Original Medicare would traditionally cover without question. Common areas of contention include:
- Inpatient rehabilitation stays.
- Skilled nursing facility (SNF) transitions.
- High-cost diagnostic imaging (MRIs, PET scans).
- Specialty medications for chronic conditions.
The Impact of AI in Claims Processing
A developing concern in recent years has been the use of automated algorithms and artificial intelligence to process these authorizations. If these tools are calibrated to prioritize cost-savings over clinical guidelines, they can result in systemic denials. Beneficiaries must be prepared to engage in the appeals process—a multi-level system that can be time-consuming and stressful during a medical crisis.
The "Trap Door" Effect: Returning to Original Medicare
Perhaps the most misunderstood Medicare Advantage problem is the difficulty of leaving a plan once your health needs change. This is often referred to as the "Medicare Advantage Trap."
Medigap Underwriting Rules
When you first enroll in Medicare Part B, you have a six-month "Medigap Open Enrollment Period." During this time, private insurers must sell you a Medicare Supplement (Medigap) policy regardless of your health status (guaranteed issue). However, if you choose a Medicare Advantage plan instead and stay in it for more than 12 months, you generally lose those federal guaranteed issue rights.
If you decide in 2026 that you want to switch back to Original Medicare because your Medicare Advantage plan denied a specific treatment or your doctor left the network, you will likely have to undergo medical underwriting to buy a Medigap plan. In most states, the insurance company can look at your medical history and:
- Charge you a much higher premium.
- Exclude coverage for your pre-existing conditions for a period.
- Deny you coverage entirely.
This leaves many sick beneficiaries "trapped" in their Medicare Advantage plans because they cannot afford the 20% coinsurance of Original Medicare without a supplement.
Financial Risks and High Out-of-Pocket Costs
Medicare Advantage plans are marketed as "zero-premium" or low-cost options. While this is true for the monthly premium, the actual cost of care can be high if you become seriously ill.
The Maximum Out-of-Pocket (MOOP) Limit
Every Medicare Advantage plan has an annual limit on what you pay for covered services (the MOOP). In 2026, these limits remain high, often reaching the federal ceiling ($9,350 for in-network services for many plans). While this protects you from unlimited financial liability, hitting a $9,000 limit in a single year can be devastating for a retiree on a fixed income.
Copayments vs. Coinsurance
In Original Medicare with a Medigap Plan G, your out-of-pocket costs are essentially capped at the Part B deductible. In Medicare Advantage, you pay copayments for almost every interaction: $35 for a specialist, $300 for an ambulance, $400 per day for a hospital stay, and 20% coinsurance for chemotherapy or dialysis. For chronic or acute conditions, these "small" costs accumulate rapidly until the MOOP is reached.
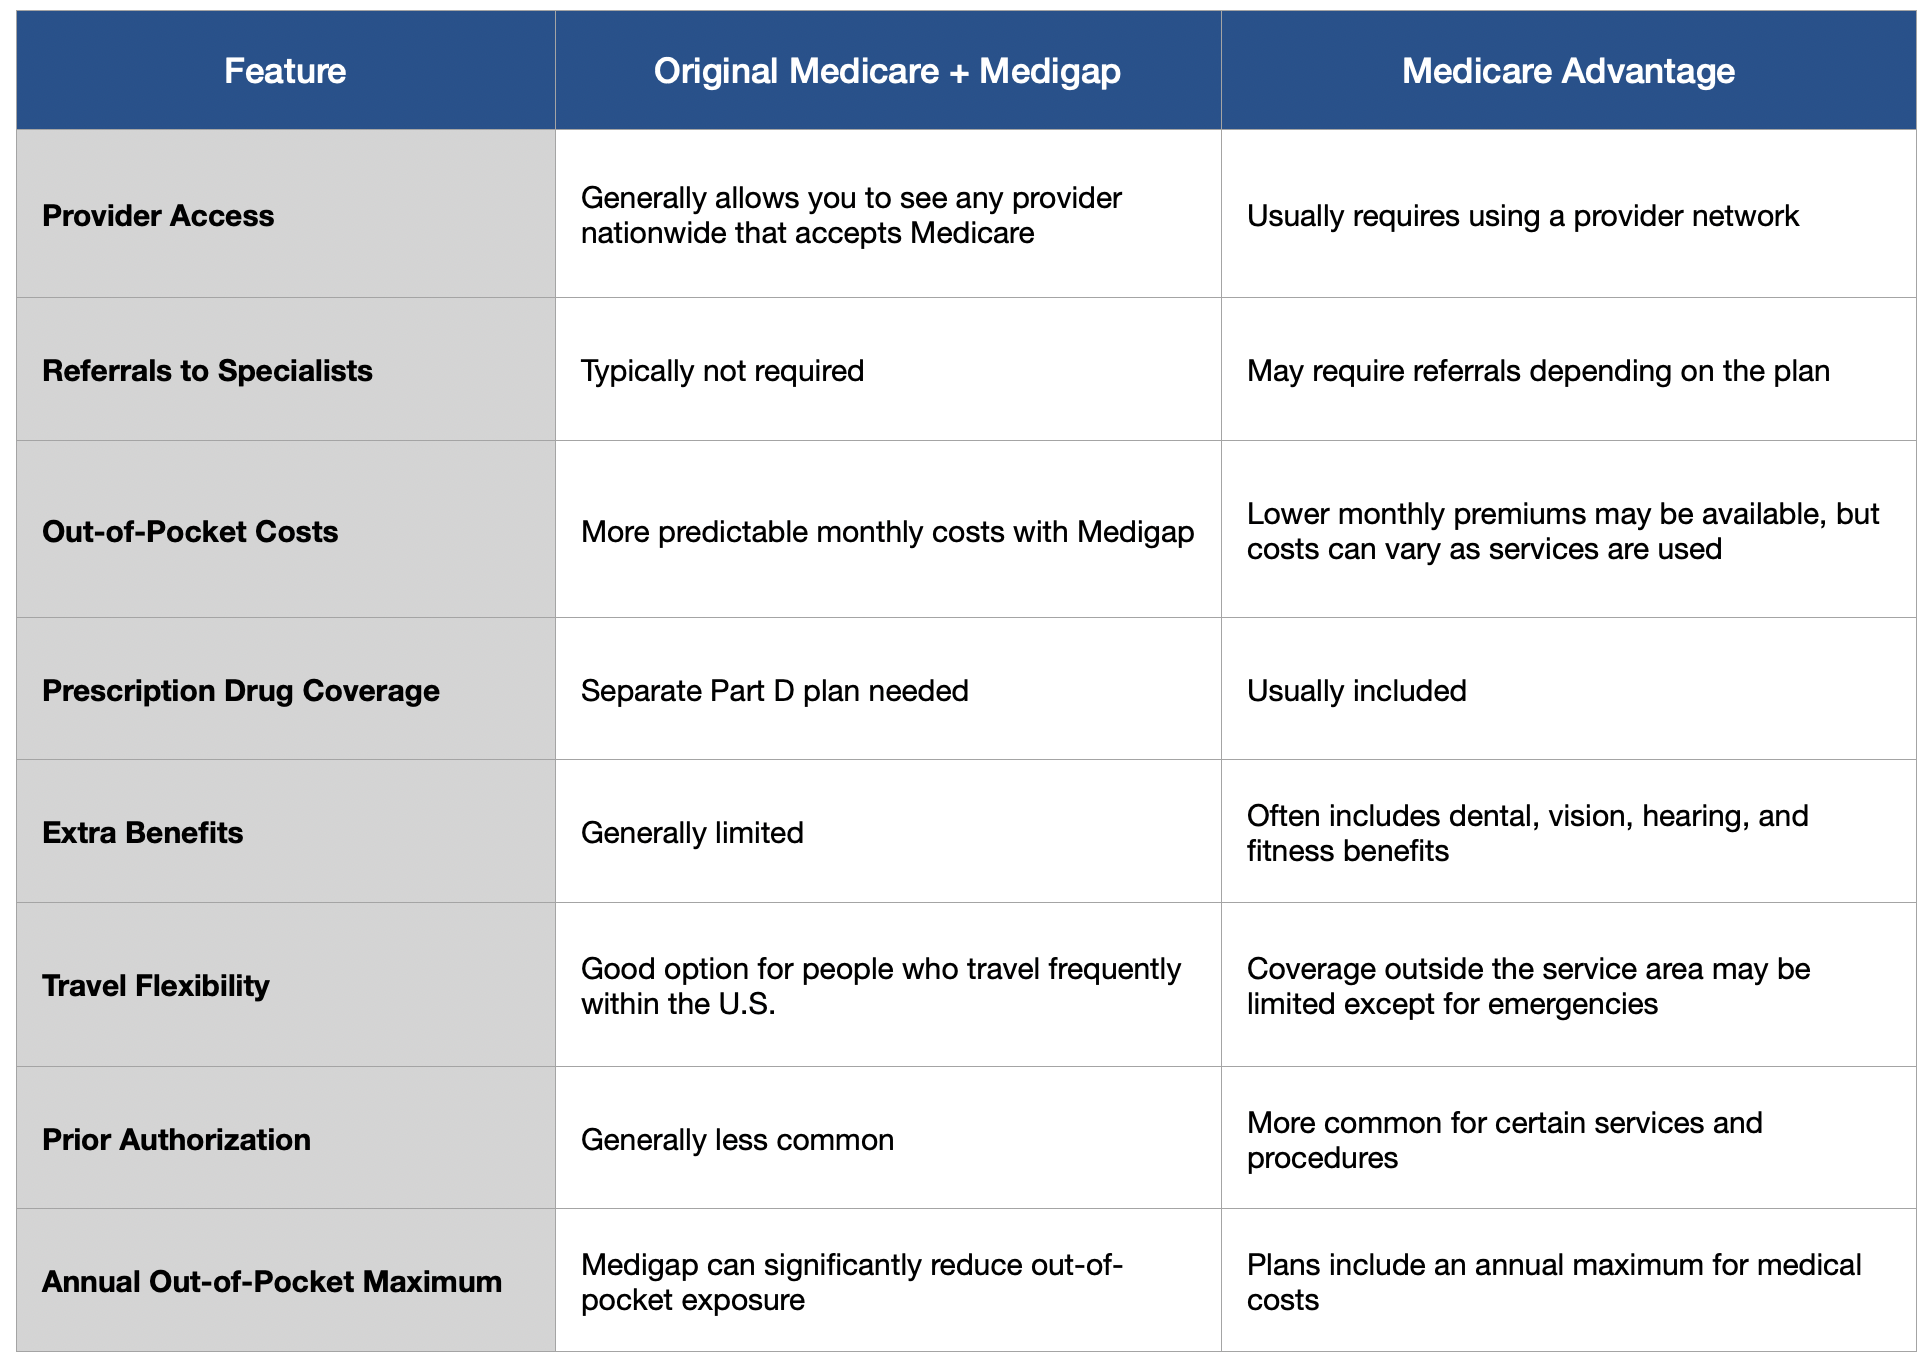
| Feature | Original Medicare + Medigap (Plan G) | Medicare Advantage (Part C) |
|---|---|---|
| Provider Choice | Any provider accepting Medicare (90%+) | Restricted to Plan Network |
| Prior Authorization | Rarely required | Frequently required for major services |
| Monthly Premium | Higher (Part B + Medigap + Part D) | Often $0 or very low |
| Out-of-Pocket Costs | Predictable (mainly Part B deductible) | Variable (copays/coinsurance up to MOOP) |
| Extra Benefits | None (Dental/Vision/Gym extra) | Included (Dental, Vision, OTC, etc.) |
| Ease of Switching | Can switch Part D yearly; Medigap harder | Can switch during AEP/OEP yearly |
Misleading Marketing and Enrollment Confusion
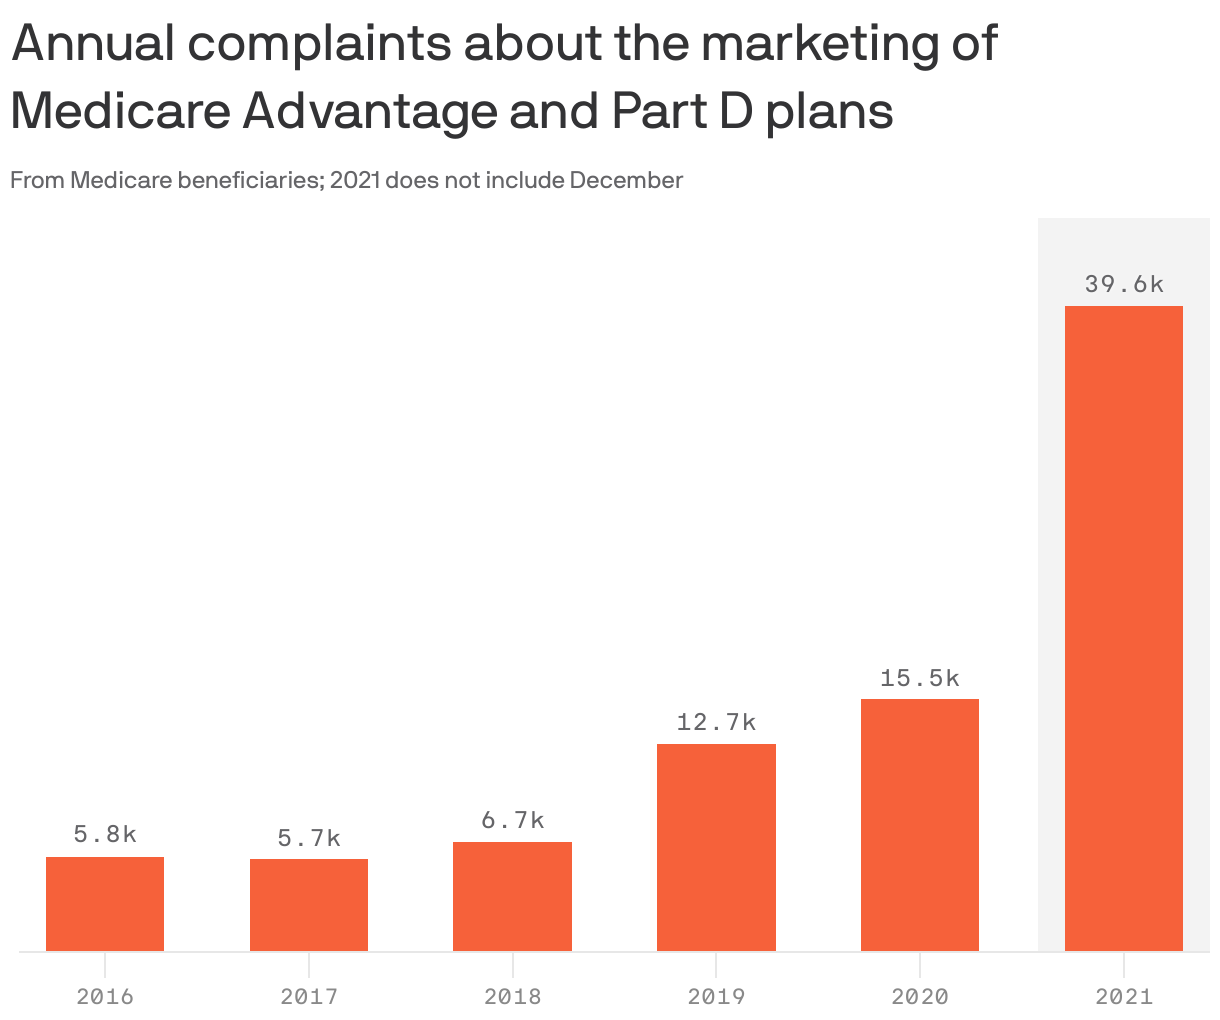
The Medicare Advantage market is highly competitive, leading to aggressive marketing tactics that often obscure the downsides of the plans.
The "Free" Benefit Allure
Advertisements often highlight "flex cards" for groceries or "money back in your Social Security check." These benefits are often highly restricted by zip code, income level, or health status. Beneficiaries frequently enroll based on these perks only to find that their lifelong specialist is no longer covered by the new plan.
Regulatory Oversight in 2026
CMS has increased oversight of "Third-Party Marketing Organizations" (TPMOs) to curb misleading television ads and cold calls. However, the burden remains on the consumer to verify if their specific medications and doctors are covered by a plan before signing up. Checking the Medicare.gov Plan Finder is the only reliable way to verify these details.
Troubleshooting and Solutions for Beneficiaries
If you are experiencing Medicare Advantage problems, you are not without recourse. Strategic actions can help mitigate these issues.
1. The Right to Appeal
Every beneficiary has the right to appeal a denial of coverage or payment. If a plan denies a "pre-service" request, you can request an expedited appeal, which must be decided within 72 hours. If the plan upholds its denial, the case automatically goes to an Independent Review Entity (IRE), which is not affiliated with the insurance company.
2. Utilizing SHIP Services
The State Health Insurance Assistance Programs (SHIP) provide free, unbiased counseling for Medicare beneficiaries. These experts can help navigate the complexities of appeals, network issues, and switching plans. You can find your local office via the SHIP National Network.
3. Exploiting the Open Enrollment Periods
If you are unhappy with your Medicare Advantage plan, you have two primary windows to make changes:
- Annual Enrollment Period (Oct 15 – Dec 7): Switch to a different MA plan or return to Original Medicare.
- Medicare Advantage Open Enrollment Period (Jan 1 – Mar 31): Specifically for those already in an MA plan to switch to another MA plan or return to Original Medicare.
Frequently Asked Questions
Why did my doctor leave my Medicare Advantage network?
Insurance companies and healthcare systems renegotiate contracts annually. If they cannot agree on reimbursement rates, the provider may leave the network. Unlike Original Medicare, where the relationship is between the doctor and the government, in Part C, it is a private business contract that can terminate at any time, sometimes even in the middle of a plan year.
Can I be denied a Medicare Advantage plan for having cancer or heart disease?
No. Since the implementation of the Affordable Care Act, Medicare Advantage plans cannot deny you coverage based on pre-existing conditions. This is a primary difference between Medicare Advantage (which must take you) and Medigap (which can deny you after your initial enrollment period).
Is prior authorization always required?
No, but it is common for "high-cost" items. Routine office visits, preventative screenings, and emergency room visits generally do not require prior authorization. However, any surgery, specialized scan, or home health care will almost certainly require the plan's "stamp of approval" before proceeding.
What happens if I move out of the plan's service area?
Medicare Advantage plans are zip-code specific. If you move out of the service area, you will trigger a Special Enrollment Period (SEP). This allows you to join a new plan in your new area or return to Original Medicare. In this specific scenario, many states provide a "guaranteed issue" right to buy a Medigap policy because the move was involuntary regarding your coverage.
Are the "extra benefits" worth the network restrictions?
This is a subjective value judgment. For a healthy individual who uses basic dental and vision services and has no preferred specialists, the "extra benefits" may outweigh the restrictions. However, for individuals with complex chronic conditions, the "extra benefits" are often worth far less than the freedom to choose any specialist and avoid the prior authorization hurdles found in Original Medicare.
Summary of Actionable Steps
To avoid the most common Medicare Advantage problems in 2026, follow these proactive steps:
- Verify Networks Directly: Never trust a printed directory. Call your doctor’s billing office and ask, "Are you in-network with the [Specific Plan Name] for 2026?"
- Check the Formulary: Ensure every one of your medications is not only covered but placed on a cost-effective "tier" in the plan’s drug list.
- Understand the MOOP: Ensure you have enough savings to cover the plan's Maximum Out-of-Pocket limit in the event of a catastrophic illness.
- Document Denials: If a service is denied, ask for the denial in writing and immediately contact your physician to start the "peer-to-peer" review or formal appeal process.
The "best" Medicare plan is not the one with the most flashy commercials, but the one that provides reliable access to the doctors you need at a cost you can sustain through both health and illness.
Image Gallery
Select an image to open it in a new tab.


Lars Thomsen
Global Labor Markets and Economic Strategy Editor
