How to Help Opiate Withdrawal Safely: A Comprehensive Medical and Supportive Guide
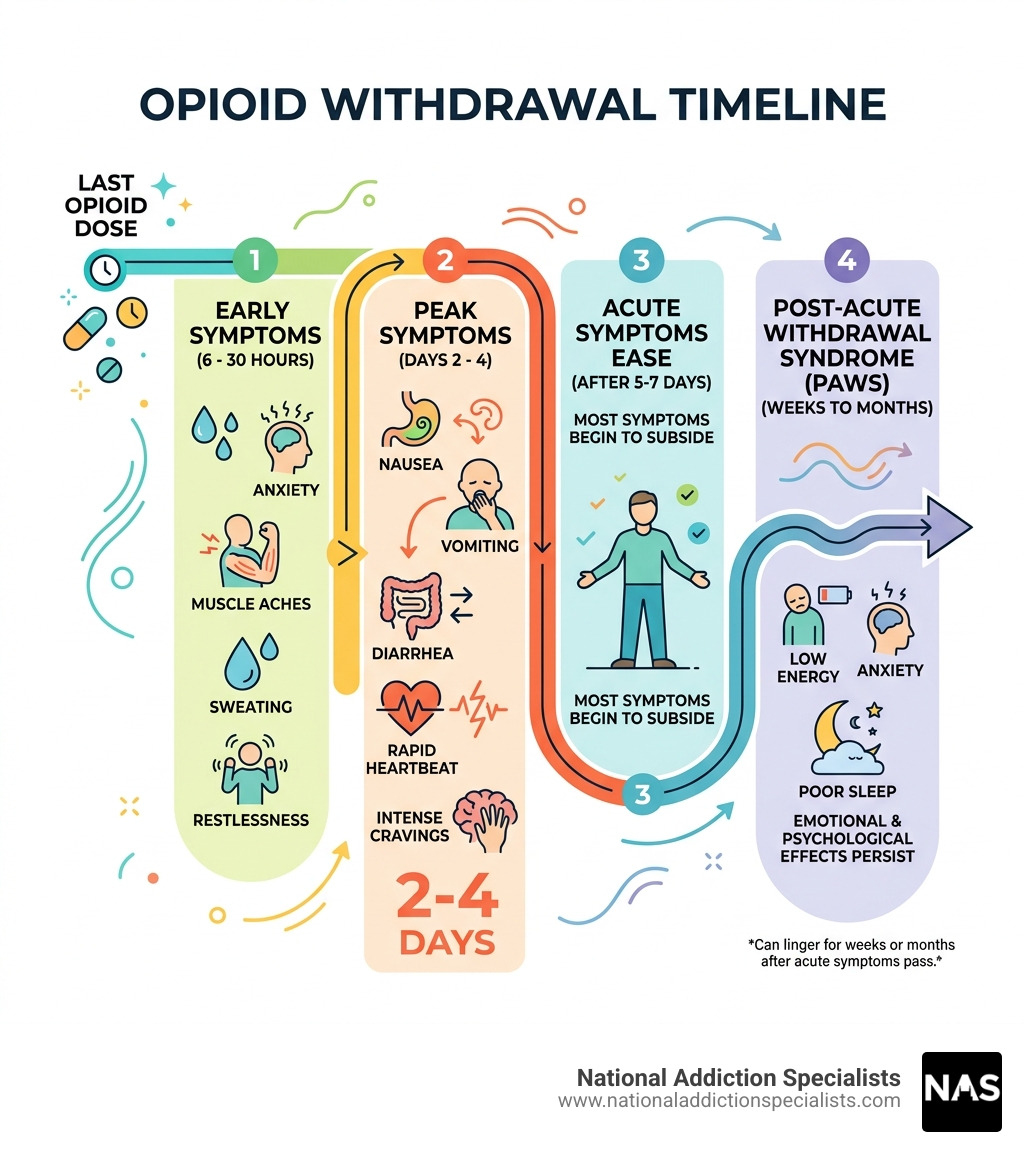
Opiate withdrawal is safely managed through a combination of professional medical supervision, Medication-Assisted Treatment (MAT) such as buprenorphine or methadone, and rigorous supportive care to manage physical symptoms. Attempting to quit "cold turkey" without clinical guidance is rarely successful and can lead to severe dehydration or a high risk of fatal relapse due to lowered tolerance.
The process of withdrawing from opioids—whether they are prescription painkillers like oxycodone or illicit substances like heroin and fentanyl—is one of the most physically and mentally taxing experiences a person can endure. In 2026, the medical community emphasizes that withdrawal is not merely a test of willpower but a physiological transition that requires specific pharmacological and environmental interventions. To help someone through this process safely, one must understand the biological timeline, the clinical tools available, and the psychological triggers that often lead to setback.
Understanding the Biological Mechanism of Opiate Withdrawal
To provide safe assistance, it is critical to understand what is happening inside the body. Opioids bind to mu-opioid receptors in the brain, suppressing the production of norepinephrine and interfering with the body's natural pain-regulation system. Over time, the brain adjusts to the presence of the drug. When the drug is suddenly removed, the nervous system goes into a state of hyper-arousal. This "rebound effect" causes the hallmark symptoms of withdrawal: racing heart, anxiety, muscle spasms, and gastrointestinal distress.
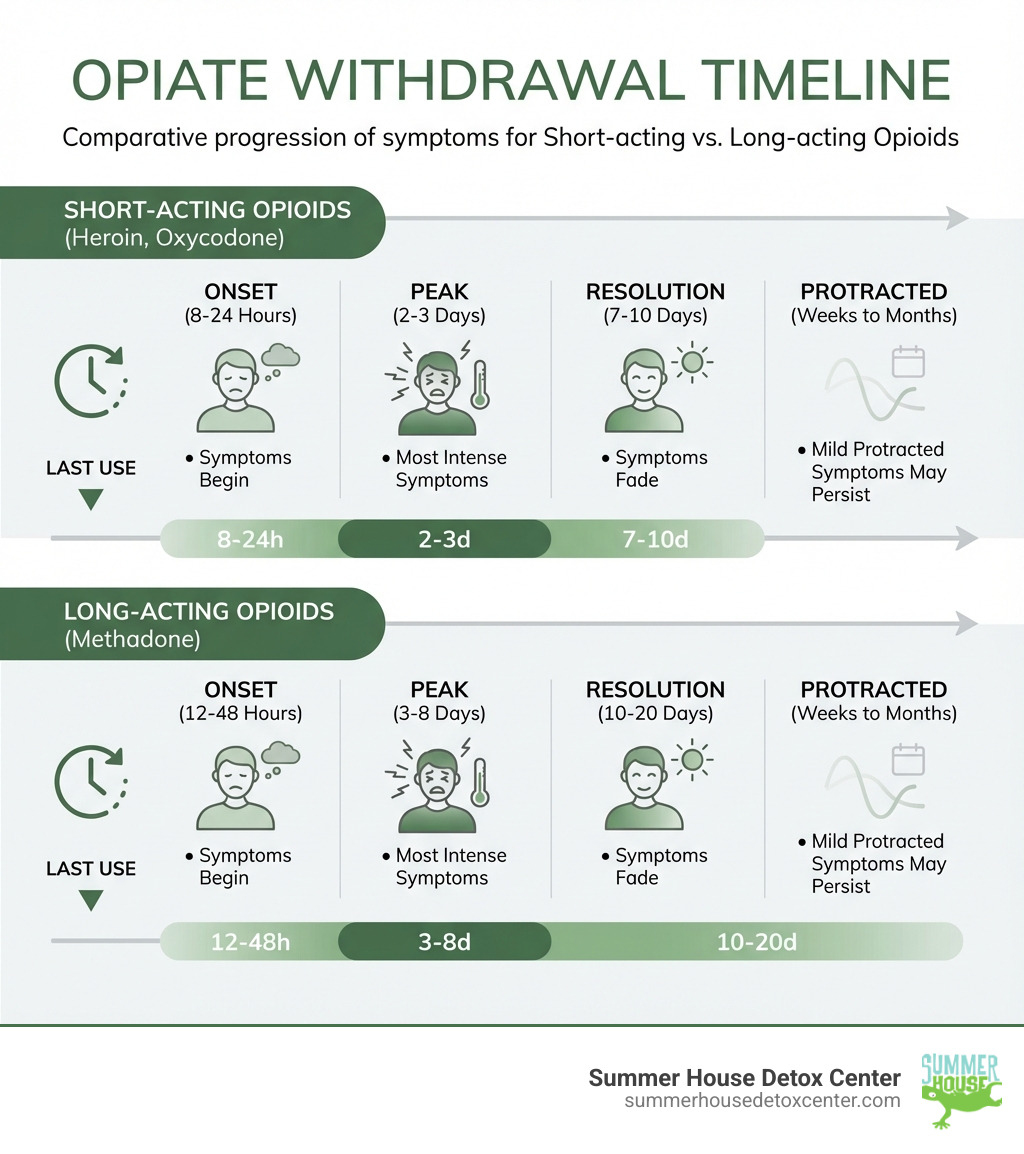
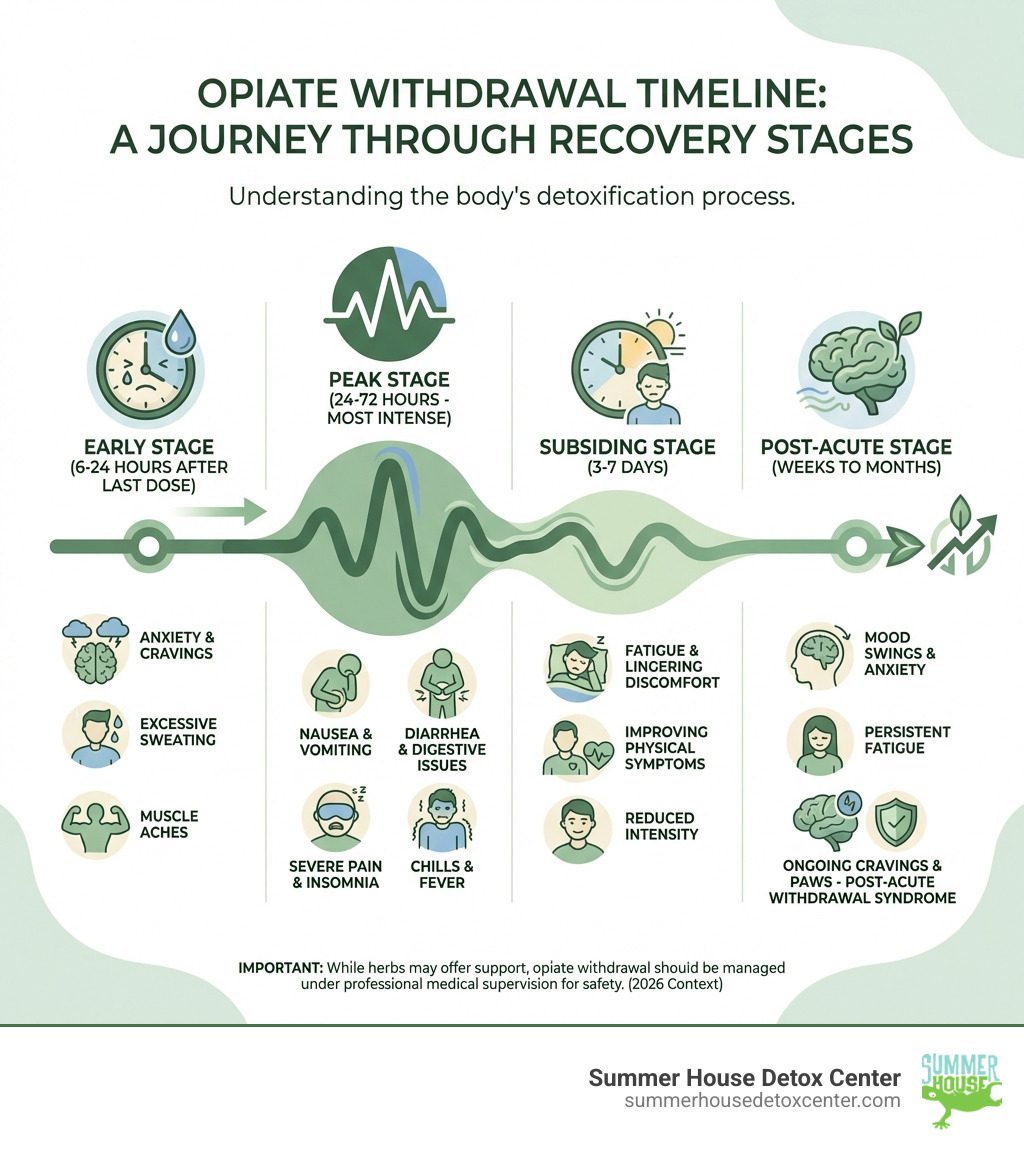
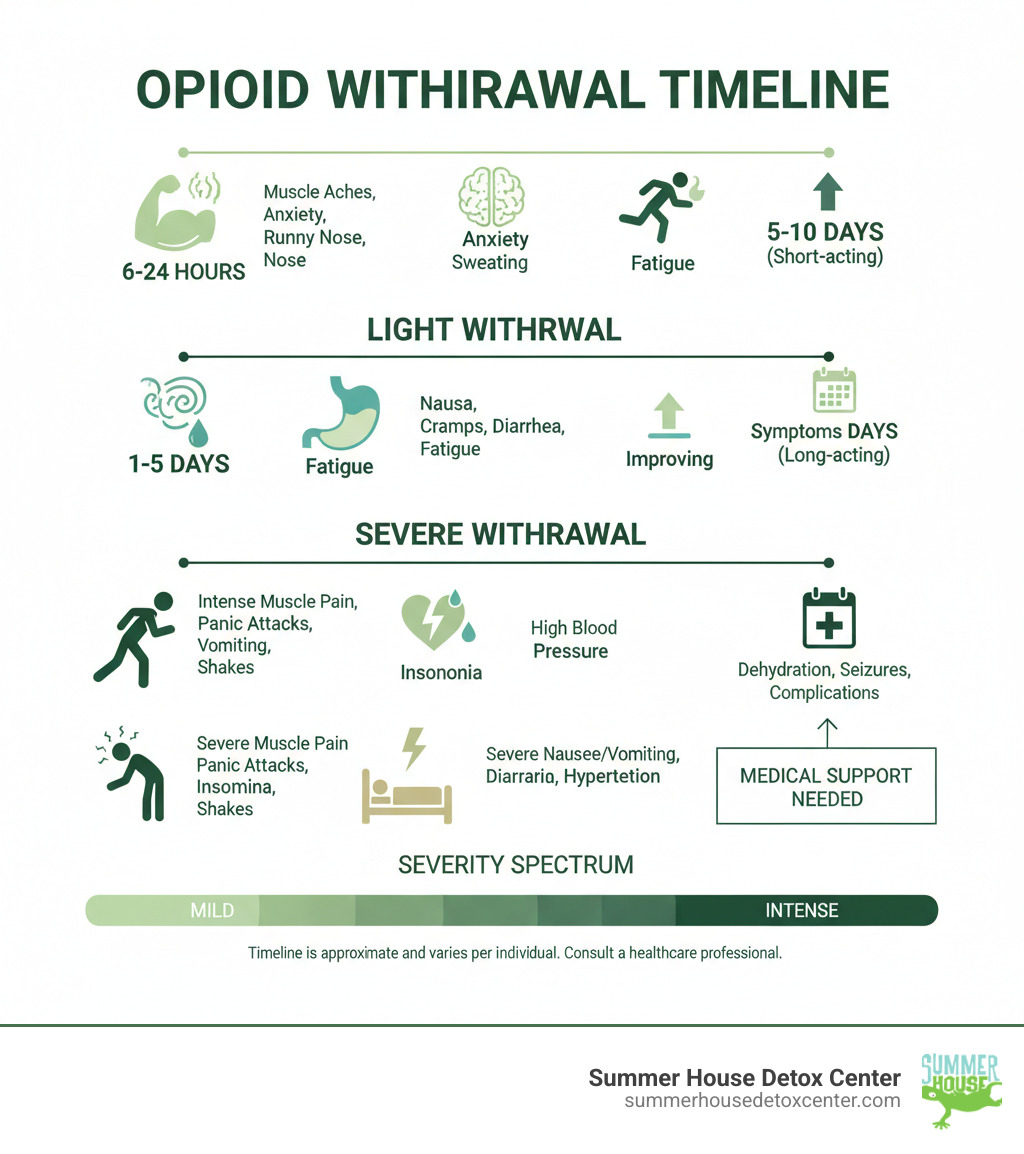
The severity and duration of withdrawal depend on the specific substance used. Short-acting opioids like heroin or immediate-release oxycodone typically produce symptoms within 6 to 12 hours of the last dose. Long-acting opioids, such as methadone or extended-release formulations, may not result in withdrawal symptoms for 24 to 48 hours. Regardless of the substance, the primary safety concern during the acute phase is the management of physical stability and the prevention of dehydration.
The Clinical Opiate Withdrawal Scale (COWS)
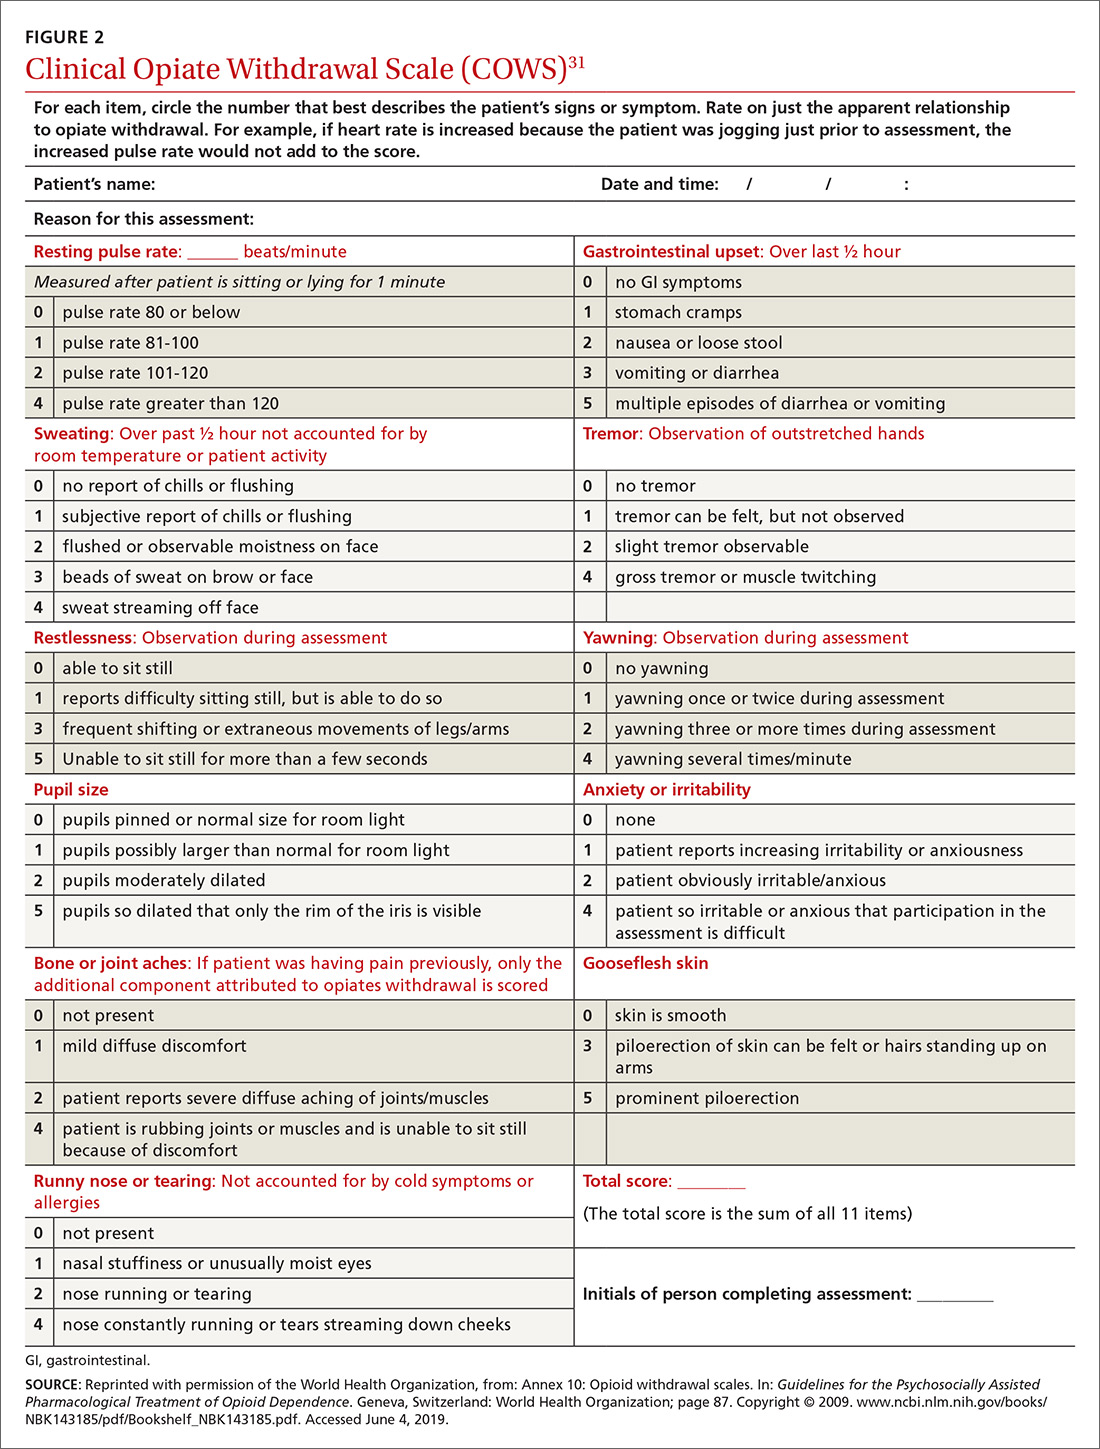
Medical professionals use the Clinical Opiate Withdrawal Scale (COWS) to objectively measure the severity of a patient's symptoms. If you are helping someone at home under a doctor's guidance, understanding these metrics is vital. The scale tracks eleven symptoms, including resting pulse rate, sweating, pupil size, bone or joint aches, and tremors.
By monitoring these signs, caregivers can determine when it is appropriate to initiate certain medications. For example, starting buprenorphine too early can trigger "precipitated withdrawal," an intense and sudden onset of symptoms that is much worse than natural withdrawal. Safety in this context means patience and precise timing based on observable clinical data.
The Gold Standard: Medication-Assisted Treatment (MAT)
In 2026, the consensus among global health organizations, including the World Health Organization, is that Medication-Assisted Treatment (MAT) is the safest and most effective way to help someone navigate opiate withdrawal. MAT uses FDA-approved medications to stabilize brain chemistry, block the euphoric effects of opioids, and relieve physiological cravings.
Buprenorphine (Suboxone)
Buprenorphine is a partial opioid agonist. It attaches to the same receptors as the opiate but does not produce the same "high." This effectively "tricks" the brain into thinking it has received the drug, which halts withdrawal symptoms. Because it has a "ceiling effect," the risk of respiratory depression is significantly lower than with full agonists, making it a safer option for many outpatients.
Methadone
Methadone is a long-acting full opioid agonist. It has been used for decades to help people transition off shorter-acting, more dangerous opioids. Because it is highly regulated and usually dispensed through certified clinics, it provides a structured environment for those who need daily monitoring and support.
Lofexidine (Lucemyra)
Lofexidine is a non-opioid medication specifically designed to treat the physical symptoms of withdrawal. It works by reducing the release of norepinephrine, which helps stabilize heart rate and blood pressure while reducing the "inner restlessness" (akathisia) that often leads patients to abandon the detox process.

Safe Supportive Care and Home Management
While medical intervention is the primary pillar of safety, supportive care addresses the immediate physical discomforts that medications may not fully cover. If a person is undergoing supervised outpatient detox, the home environment must be optimized for safety and comfort.
Hydration and Electrolyte Balance
The most significant physical danger during opiate withdrawal is dehydration. Persistent vomiting and diarrhea can lead to rapid loss of fluids and essential minerals like potassium and sodium. Caregivers should provide oral rehydration solutions rather than just plain water. In 2026, many recovery specialists recommend medical-grade electrolyte drinks to prevent cardiac arrhythmias associated with severe electrolyte depletion.
Managing Gastrointestinal and Physical Distress
Over-the-counter medications can be used, but only under the advice of a physician to ensure they do not interact with MAT protocols.
- Loperamide: Used for diarrhea, but it must be used strictly according to the label. In high doses, it can cause dangerous heart rhythm issues.
- NSAIDs: Medications like ibuprofen can help with the significant bone and muscle aches characteristic of "kicking the habit."
- Antiemetics: Prescription medications like Ondansetron (Zofran) may be necessary if the individual cannot keep down fluids or oral medications.
Environmental Optimization
The individual’s nervous system will be hypersensitive. A safe environment is one that is quiet, dim, and temperature-controlled. Use heavy blankets for "restless legs" and ensure there are clean clothes and linens available, as "drenching sweats" are a common and recurring symptom.
Comparison of Detox Settings
Choosing the right environment is a major factor in how safely a person can withdraw. The following table compares the three most common settings available in 2026.
| Feature | Inpatient Medical Detox | Partial Hospitalization (PHP) | Supervised Outpatient |
|---|---|---|---|
| Level of Safety | Highest; 24/7 medical monitoring. | High; daily clinical check-ins. | Moderate; relies on home support. |
| Medical Access | Immediate IV fluids and Rx adjustments. | Daily access to physicians. | Scheduled appointments/Telehealth. |
| Cost (Estimated) | High ($500–$1,000+ per day). | Moderate ($250–$500 per day). | Lower (varies by Rx/insurance). |
| Success Rate | Highest for initial stabilization. | Good for transition to therapy. | High for highly motivated individuals. |
| Best For | History of seizures, polydrug use. | Moderate OUD with stable housing. | Mild OUD or significant work duties. |
The Psychological Safety Net: Preventing Relapse
The "safety" of withdrawal is not just about surviving the first seven days; it is about preventing a fatal overdose immediately after. When a person goes through withdrawal, their physical tolerance to opioids drops almost to zero. If they experience a lapse in judgment and return to their previous dosage, that dose is now likely to be lethal.
The Role of Naloxone (Narcan)
Anyone helping someone through withdrawal must have Naloxone on hand. Naloxone is an opioid antagonist that can reverse an overdose by stripping the opioids off the receptors in the brain. In 2026, it is widely available over-the-counter and is a non-negotiable component of a safe withdrawal environment.
Addressing Post-Acute Withdrawal Syndrome (PAWS)
Safety also includes managing the psychological symptoms that follow the physical ones. Post-Acute Withdrawal Syndrome (PAWS) can last for months and includes symptoms like deep depression, insomnia, and anhedonia (the inability to feel pleasure). Without a plan for mental health support—such as Cognitive Behavioral Therapy (CBT) or 12-step programs—the risk of suicide or relapse remains elevated.
Peer Support and Telehealth
Advancements in telehealth as of 2026 have made it easier for those in withdrawal to access peer support specialists and counselors without leaving their homes. Regular check-ins with a therapist or a support group like Narcotics Anonymous (NA) provide an emotional safety valve, reducing the feeling of isolation that often triggers a return to use.
Essential Steps for a Safe Withdrawal Plan
To help someone effectively, follow this sequence of actions to ensure no safety measures are overlooked:
- Consult a Professional: Before stopping any medication, speak with an addiction specialist or a primary care doctor. They will evaluate whether inpatient or outpatient care is appropriate.
- Secure the Environment: Remove all substances, paraphernalia, and "triggers" from the home. Ensure Naloxone is accessible and that the caregiver knows how to use it.
- Establish a Medication Schedule: If MAT is prescribed, follow the dosing instructions exactly. Do not skip doses to "test" progress, as this can lead to instability.
- Monitor Vitals: Keep a log of heart rate, temperature, and fluid intake. If the heart rate exceeds 120 bpm or the person becomes delirious, seek emergency medical attention immediately.
- Plan for Aftercare: Withdrawal is only the first step. Safety is maintained through long-term treatment, which may include months or years of maintenance medication and counseling.
Common Risks and How to Mitigate Them
One of the most dangerous myths is that "natural" or "holistic" detoxes are safer. In reality, unregulated supplements can interact poorly with the body's already stressed systems.
- Aspiration Risk: If a person is heavily sedated or very weak and begins to vomit, they are at risk of inhaling vomit into their lungs (aspiration). Safe positioning (lying on the side) is essential.
- Cardiac Stress: The surge in adrenaline during withdrawal can be dangerous for those with underlying heart conditions. This is why a pre-detox EKG is often recommended by SAMHSA guidelines.
- Mental Health Crisis: Withdrawal often unmasks underlying bipolar disorder, PTSD, or clinical depression. A safety plan must include a contact number for a crisis intervention team.
Frequently Asked Questions
Can you die from opiate withdrawal?
While opiate withdrawal is rarely fatal in a direct sense (unlike alcohol or benzodiazepine withdrawal), it can be life-threatening if not managed. The primary causes of death during withdrawal are dehydration and electrolyte imbalance leading to heart failure, or aspiration of vomit. The greatest risk, however, is a fatal overdose if the person relapses shortly after detoxing.
How long does the "worst" part of withdrawal last?
For short-acting opioids, the physical peak usually occurs between 48 and 72 hours. For long-acting opioids like methadone, the peak might not occur until the 5th or 6th day. By the end of the first week, most physical symptoms begin to subside, though psychological cravings and fatigue may persist for much longer.
Is it safe to use Suboxone to help with withdrawal?
Yes, when used under medical supervision, Suboxone (buprenorphine/naloxone) is considered one of the safest ways to manage withdrawal. It prevents the "crash" of the nervous system and allows the individual to function and participate in therapy while their brain chemistry heals.
What should I put in a "Withdrawal Kit"?
A safe kit includes: medical-grade electrolytes, high-protein/low-fiber snacks, over-the-counter pain relievers (approved by a doctor), clean linens, a thermometer, a blood pressure cuff, and Naloxone. Having these ready prevents the need to leave the house during the most difficult phase of the process.
Can I help someone withdraw if they don't want to go to a clinic?
While outpatient detox is possible, it still requires a doctor's prescription for the necessary safety medications. You can support them by managing their environment and hydration, but professional medical oversight is required to ensure they have the pharmacological support needed to prevent dangerous complications.
Final Recommendation for Safe Recovery
The safest way to help someone through opiate withdrawal is to bridge the gap between home support and professional medical care. Never attempt to manage a severe opioid use disorder alone. In 2026, the availability of telehealth and specialized detox clinics means that professional help is more accessible than ever. Reach out to a certified addiction specialist to create a tapering or MAT plan that minimizes physical pain and maximizes the chances of long-term success.
Image Gallery
Select an image to open it in a new tab.
Celine Dubois
Contemporary Living and Global Arts Columnist
