5 GLP-2 Medications on the Market: Comprehensive Guide for 2026
As of 2026, the primary GLP-2 medications available or in late-stage commercial use include Teduglutide, Apraglutide, Gleapaglutide, Efocipegtrutide, and Dapiglutide. These therapies primarily treat Short Bowel Syndrome (SBS) by enhancing intestinal absorption, promoting mucosal growth, and reducing dependency on parenteral nutrition through the activation of the glucagon-like peptide-2 receptor.
Understanding the Role of GLP-2 in Intestinal Health
Glucagon-like peptide-2 (GLP-2) is a 33-amino acid peptide hormone naturally secreted by the L-cells of the distal ileum and colon in response to nutrient ingestion. In a healthy digestive system, GLP-2 serves as a critical trophic hormone, meaning it stimulates the growth and maintenance of the intestinal lining. It specifically targets the crypt cells in the intestinal epithelium, promoting proliferation and inhibiting apoptosis (cell death).
For patients suffering from Short Bowel Syndrome (SBS)—a condition often resulting from surgical resection due to Crohn’s disease, mesenteric ischemia, or congenital defects—the natural production of GLP-2 is frequently insufficient. This leads to malabsorption, where the remaining intestine cannot absorb enough fluids and nutrients to sustain life, necessitating Parenteral Nutrition (PN) or Intravenous Fluids (IVF).
GLP-2 medications, also known as GLP-2 analogs, are engineered to mimic or enhance this natural process. By binding to GLP-2 receptors, these medications increase the surface area of the gut by lengthening the intestinal villi (tiny, finger-like projections), slowing gastric emptying, and increasing intestinal blood flow. In 2026, the therapeutic landscape has expanded from daily injections to long-acting formulations that significantly improve patient quality of life.
1. Teduglutide (Gattex/Revestive)
Teduglutide remains the foundational GLP-2 analog in 2026. Approved by the FDA in 2012 under the brand name Gattex, it was the first medication specifically designed to reduce PN dependency in patients with SBS.
Mechanism and Administration
Teduglutide is a recombinant analog of human GLP-2. It differs from naturally occurring GLP-2 by a single amino acid substitution (alanine to glycine), which makes it resistant to degradation by the enzyme dipeptidyl peptidase-IV (DPP-IV). This modification extends its half-life from approximately seven minutes to about two hours.
Despite this extension, Teduglutide still requires once-daily subcutaneous injections. For many patients, this remains a significant burden, though the clinical results are robust.
Efficacy and Clinical Outcomes
Clinical trials and long-term registry data through 2026 show that Teduglutide can reduce PN volume by 20% to 100% in responsive patients.
- PN Reduction: Approximately 60-70% of patients achieve a reduction of at least 20% in PN volume after 24 weeks.
- Enteral Autonomy: A subset of patients (roughly 10-15%) can achieve complete independence from parenteral nutrition over multi-year treatment periods.
Safety and Monitoring
Because Teduglutide promotes cell growth, there is a theoretical risk of accelerating the growth of pre-existing neoplasms. In 2026, standard protocol requires a colonoscopy within six months prior to starting treatment and periodic follow-ups. Common side effects include abdominal pain, nausea, and injection site reactions.

2. Apraglutide (Yuvonri)
By 2026, Apraglutide (developed by VectivBio and later acquired by Ironwood Pharmaceuticals) has established itself as a preferred second-generation GLP-2 analog. Its primary advantage over Teduglutide is its significantly extended half-life, allowing for once-weekly dosing.
The Advantage of Once-Weekly Dosing
Apraglutide was designed specifically to address the high treatment burden of daily injections. With a half-life exceeding 30 hours, it provides sustained GLP-2 receptor activation throughout the week. This pharmacological profile leads to more consistent stimulation of the intestinal mucosa compared to the "peak and valley" effect of daily analogs.
Clinical Performance in SBS-IF
The Phase 3 STARS trial demonstrated that Apraglutide is highly effective in patients with SBS and Intestinal Failure (SBS-IF).
- Stoma vs. Colon-in-Continuity: One of the unique aspects of Apraglutide research is its focus on different anatomical subtypes. It has shown significant efficacy in patients with a "stoma" (where the colon is not connected) as well as those with "colon-in-continuity."
- Fluid Absorption: Patients treated with Apraglutide often report a dramatic decrease in fecal output and a corresponding increase in urine output, indicating better fluid absorption.
Market Positioning
In the 2026 market, Apraglutide is often prescribed to newly diagnosed SBS patients or those who find daily injections of Teduglutide unmanageable. Its safety profile is comparable to Teduglutide, focusing on gastrointestinal monitoring and gallbladder health.
3. Gleapaglutide
Gleapaglutide, developed by Zealand Pharma, is another potent, long-acting GLP-2 analog that has reached the market by 2026. Like Apraglutide, it targets the limitations of first-generation therapies.
Technical Profile and Delivery
Gleapaglutide is delivered via a customized autoinjector pen, which has been praised for its ease of use in the pediatric and elderly populations. Its chemical structure is highly stable, allowing for a concentrated formulation that requires a very low volume of liquid per injection, reducing injection site discomfort.
Clinical Significance
The pivotal trials for Gleapaglutide focused on the reduction of weekly PN volume. Key findings include:
- Rapid Response: Many patients show significant increases in intestinal absorption within the first 4 to 8 weeks of therapy.
- Dose-Dependent Increases: Gleapaglutide allows for some titration, enabling clinicians to find the minimum effective dose for maintaining enteral stability.
The 2026 guidelines suggest Gleapaglutide as a primary option for patients who require high-volume PN and have struggled with the systemic "rebound" effect sometimes seen when daily doses are missed on older medications.
4. Efocipegtrutide (HM15912)
Efocipegtrutide represents the cutting edge of long-acting GLP-2 therapy in 2026. Developed using the "LAPSCOVERY" (Long-Acting Protein/Peptide Discovery) platform, it is often categorized as a "next-generation" peptide.
Prolonged Duration of Action
While Apraglutide and Gleapaglutide moved the needle to once-weekly dosing, Efocipegtrutide has explored even longer intervals in clinical settings. Its structure involves a GLP-2 analog conjugated to a constant region of an immunoglobulin (Fc fragment), which prevents renal clearance and protects the peptide from enzymatic breakdown.
Broadening the Indication
Beyond Short Bowel Syndrome, by 2026, Efocipegtrutide has been studied for:
- Chemotherapy-Induced Diarrhea: Protecting the gut lining during aggressive cancer treatments.
- Necrotizing Enterocolitis (NEC): Use in neonatal intensive care units to promote gut healing in premature infants.
Its availability on the market in 2026 provides a critical alternative for "difficult-to-treat" SBS cases where standard GLP-2 analogs have failed to produce sufficient villus growth.
5. Dapiglutide (Dual GLP-1/GLP-2 Agonist)
The fifth entry in the 2026 GLP-2 market landscape is Dapiglutide, a dual agonist that activates both GLP-1 and GLP-2 receptors. This medication represents a paradigm shift in treating intestinal failure and associated metabolic complications.
The Dual Agonist Mechanism
While GLP-2 promotes intestinal growth, GLP-1 has its own benefits, including slowing gastric emptying (giving the gut more time to absorb nutrients) and providing anti-inflammatory effects.
- GLP-1 Component: Helps control the "dumping syndrome" often seen in SBS patients.
- GLP-2 Component: Directly stimulates mucosal regeneration.
Clinical Utility
Dapiglutide is particularly useful for patients with SBS who also struggle with glucose intolerance or severe gastric hypermotility. By 2026, it is often used as a specialized therapy for patients who need both the regenerative power of GLP-2 and the motility-regulating power of GLP-1.
Studies published through 2025 indicated that Dapiglutide might offer superior weight maintenance compared to pure GLP-2 analogs because it addresses the speed at which food moves through the remaining digestive tract.
Comparison of Available GLP-2 Medications (2026)
The following table compares the primary characteristics of the five medications discussed.
| Medication | Brand Name (2026) | Dosing Frequency | Primary Target | Key Benefit |
|---|---|---|---|---|
| Teduglutide | Gattex / Revestive | Daily | SBS-IF (Adult/Ped) | Extensive long-term safety data (10+ years). |
| Apraglutide | Yuvonri | Weekly | SBS-IF | High potency; effective in both stoma and colon-in-continuity. |
| Gleapaglutide | (Varies by region) | Weekly | SBS-IF | Low-volume injection via autoinjector; rapid absorption improvement. |
| Efocipegtrutide | Efociv | Weekly / Bi-weekly | SBS / Gut Injury | Exceptional half-life; potential for broader gut-injury indications. |
| Dapiglutide | Dapiglut | Weekly | SBS / Malabsorption | Dual GLP-1/GLP-2 action; helps manage gastric motility. |
Access and Insurance Coverage in 2026
Despite the clinical breakthroughs, access to GLP-2 medications remains a complex process due to their status as Orphan Drugs. These medications are among the most expensive chronic therapies on the market, often costing upwards of $300,000 to $500,000 per year.
Prior Authorization Requirements
In 2026, most insurance carriers (including Medicare and private payers) require strict documentation before approving GLP-2 therapy:
- Diagnosis Confirmation: Evidence of SBS-IF, typically defined as dependence on PN for at least 12 months.
- Stable PN Baseline: A period of stable PN requirements to measure the drug's effectiveness.
- Nutritionist Involvement: Documentation that enteral nutrition (oral/tube feeding) has been optimized and is still insufficient.
Patient Assistance Programs
Manufacturers of Apraglutide and Gleapaglutide have introduced robust patient support programs by 2026 to compete with the established Gattex One program. These programs often provide co-pay assistance for commercially insured patients and help navigate the "biologic coordinator" roles required at specialty pharmacies.
Future Outlook: Beyond 2026
The market for GLP-2 medications is moving toward even more personalized administration. Research is currently investigating oral GLP-2 formulations and gene therapy approaches designed to stimulate the body's own L-cells to produce supra-physiological levels of GLP-2. However, for the current 2026 calendar year, the five subcutaneous injectable therapies listed above remain the gold standard for clinical care.
Clinicians are also beginning to explore "combination peptide therapy," where GLP-2 analogs are used alongside other growth factors (like IGF-1) to maximize the "adaptation" phase following bowel surgery. This could potentially shorten the time a patient spends on PN, even in the most severe cases of "ultra-short" bowel syndrome.
Frequently Asked Questions (FAQ)
Can I switch from daily Gattex to once-weekly Apraglutide?
Yes, in 2026, "switching studies" have shown that most patients can transition from daily Teduglutide to once-weekly Apraglutide or Gleapaglutide without losing the progress made in PN reduction. However, a transition period with close monitoring of fluid status is required to prevent dehydration or electrolyte imbalances during the adjustment of dosing schedules.
Are GLP-2 medications the same as Ozempic or Wegovy?
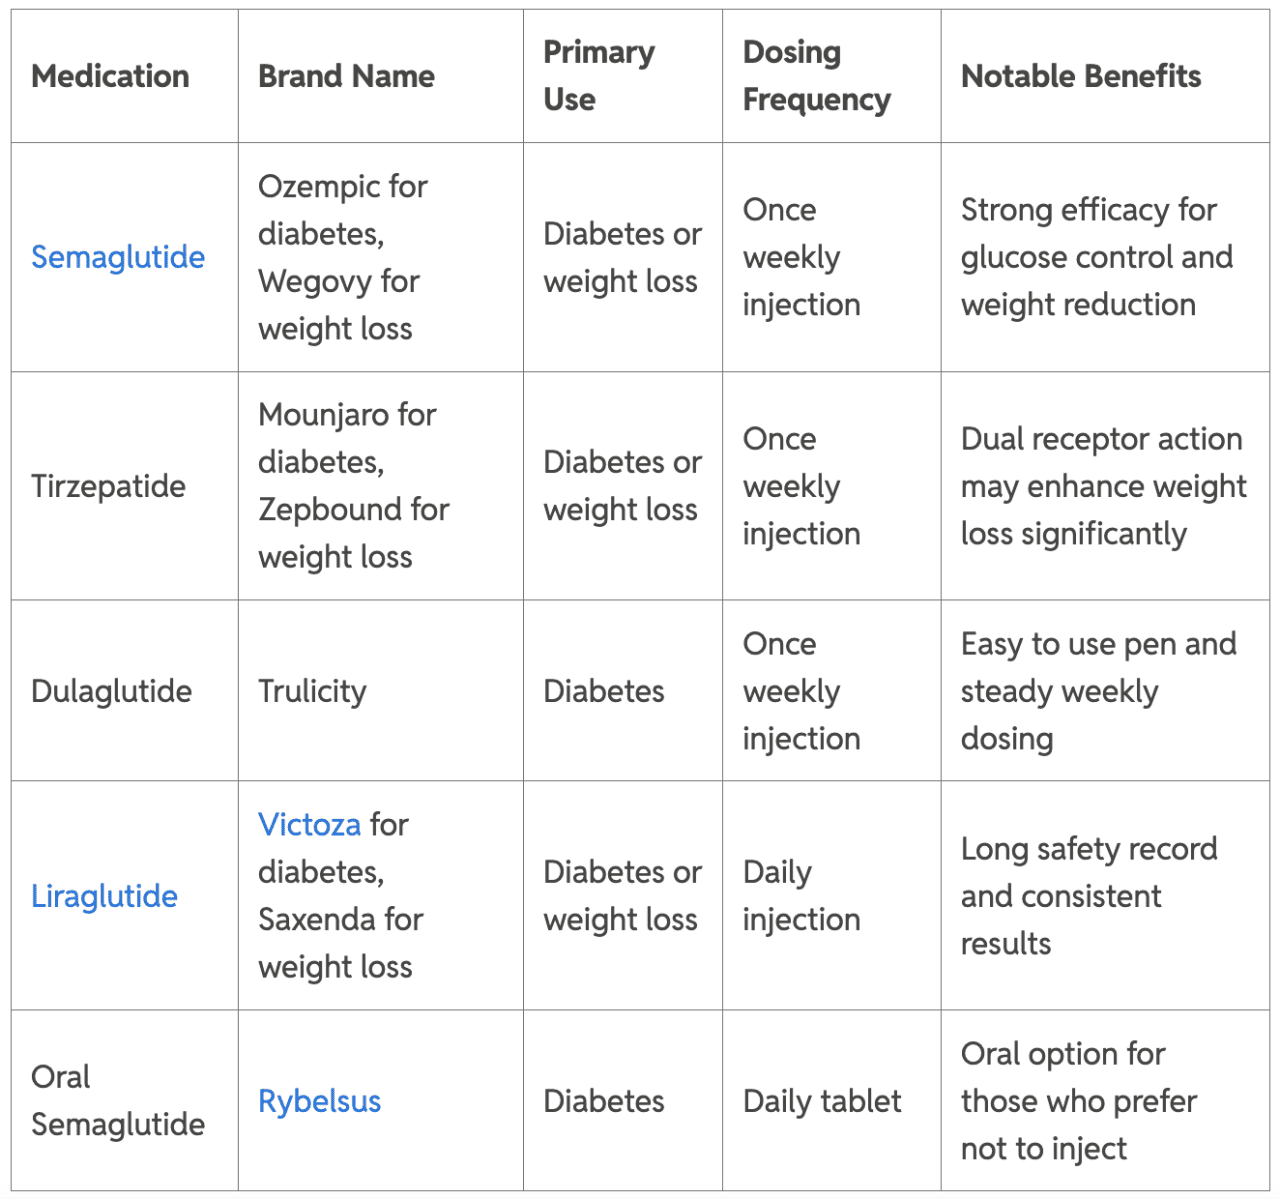
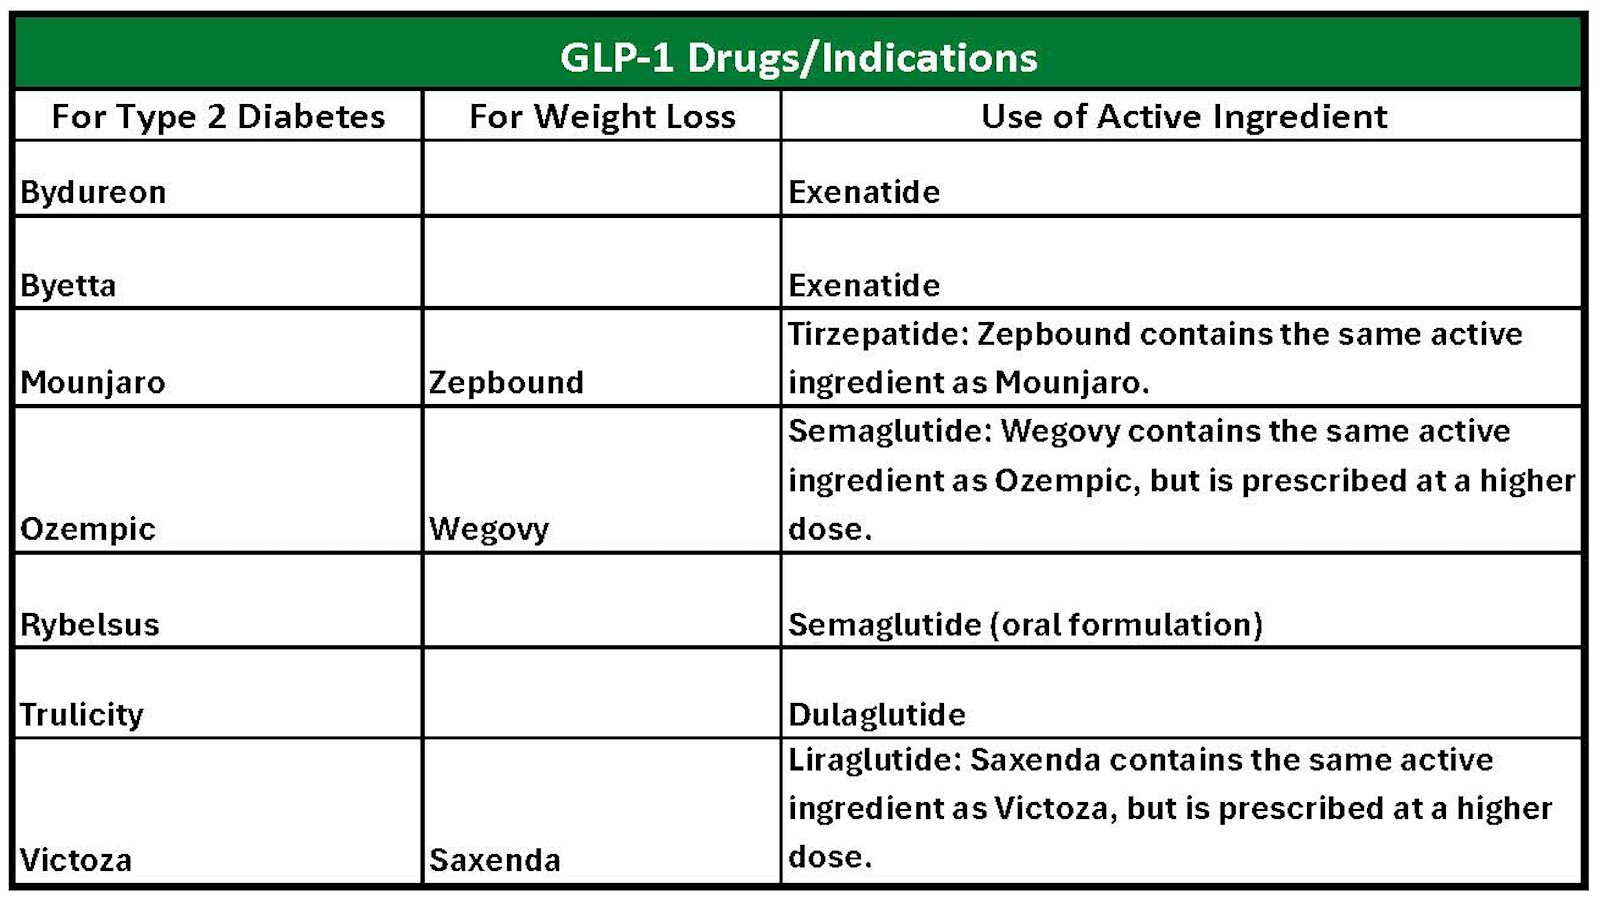
No. Ozempic and Wegovy are GLP-1 receptor agonists used for diabetes and weight loss. While they belong to the same family of "incretin" hormones, GLP-2 medications (like Gattex or Apraglutide) specifically target intestinal growth and fluid absorption. While some dual agonists like Dapiglutide activate both receptors, a standard GLP-1 drug will not provide the intestinal mucosal growth needed for SBS.
What are the main risks of long-term GLP-2 therapy?
The primary long-term risks identified by 2026 include the potential for intestinal polyps, gallbladder disease (cholecystitis), and fluid overload. Because these drugs increase absorption, some patients may experience swelling (edema) or congestive heart failure symptoms if their Parenteral Nutrition volume is not reduced quickly enough as the drug starts to work.
Are these medications available for children?
Teduglutide has had pediatric approval for several years (for ages 1 and older). By 2026, several of the newer weekly analogs (Apraglutide and Gleapaglutide) have also received or are seeking pediatric labeling, as the burden of daily injections is particularly difficult for children and their caregivers.
How do I know if the medication is working?
The most common metric for success is the reduction in PN volume. If you were previously receiving 2,000mL of IV fluids five nights a week and can safely reduce that to 1,000mL or fewer nights per week while maintaining your weight and urine output, the medication is considered effective.
Final Recommendation
If you or a loved one is living with Short Bowel Syndrome and remains dependent on parenteral nutrition, the first step is to consult with a Gastroenterologist specializing in Intestinal Rehabilitation. In 2026, the availability of five distinct GLP-2 pathways means that therapy can be tailored to your specific anatomy and lifestyle. Ask your provider for a "fecal fat" or "D-xylose" absorption test to establish a baseline, and inquire specifically about the newer once-weekly analogs to minimize the daily burden of care.
Image Gallery
Select an image to open it in a new tab.



Simon Caldwell
Enterprise Technology and Systems Editor
